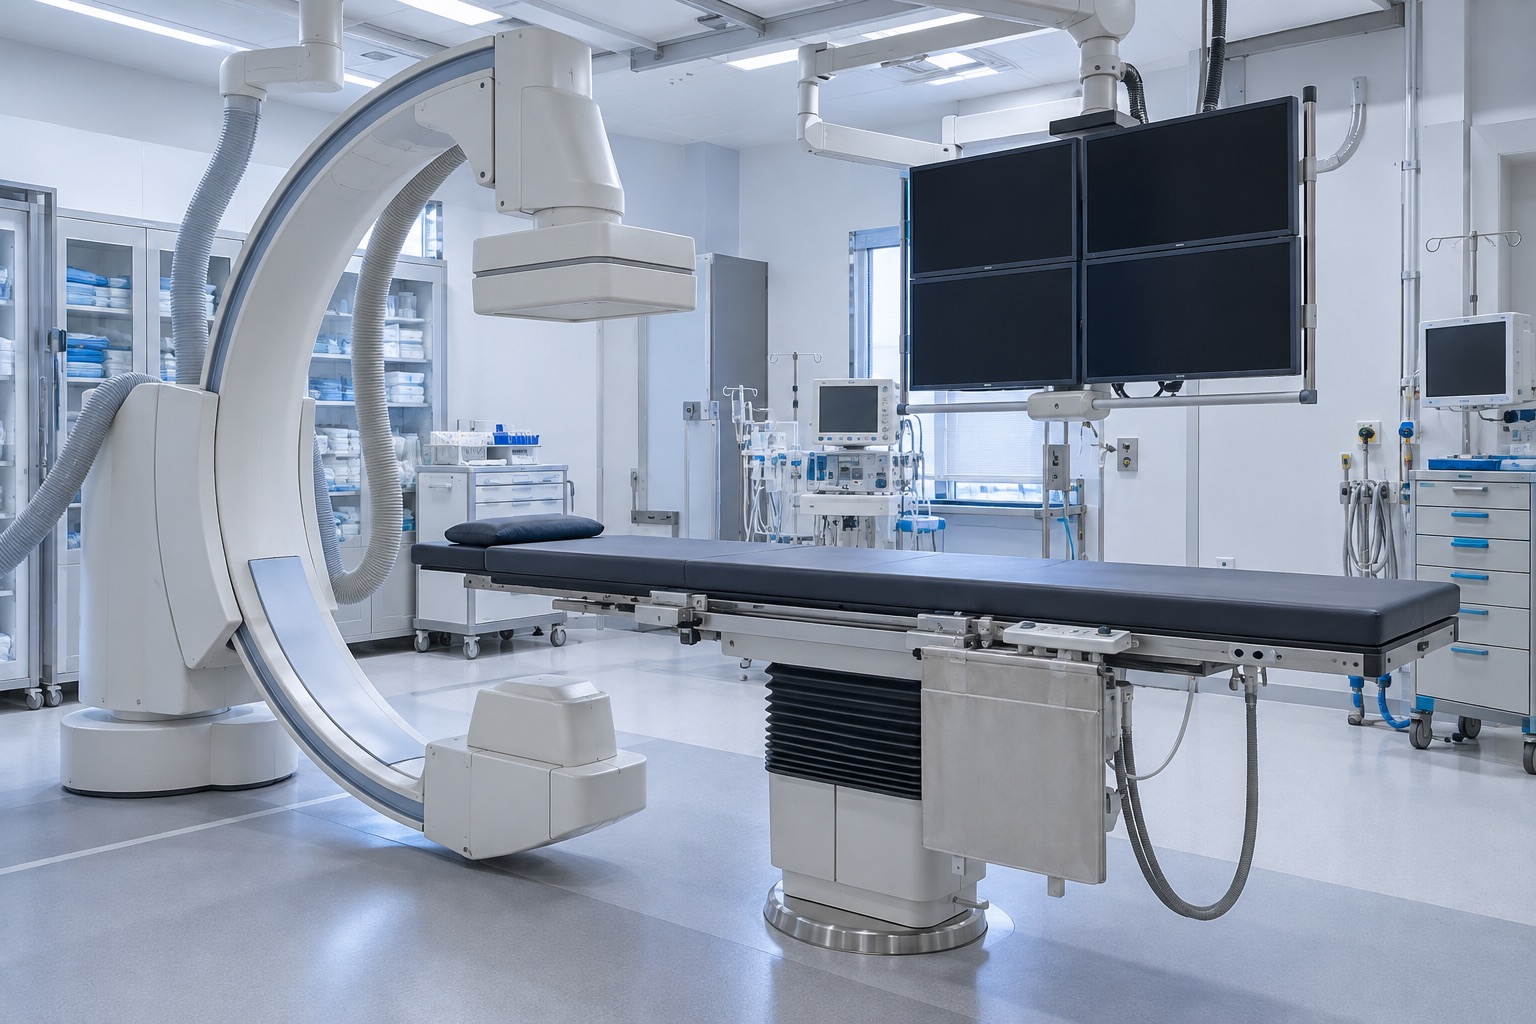
Illustrative room · equipment and treatment settings vary
01
What could it help with?
GAE blocks selected small arteries associated with knee inflammation. SIR supports it for selected patients, but a sham-controlled trial did not show a significant advantage at four months and NICE recommends research-only use. [1][2][3]
02
Who might it suit?
For: A specialist discussion of an emerging knee procedure.
Not for: An automatic choice based on an X-ray alone, or a substitute for assessment by an interventional radiologist.
03
Limits and important cautions
Evidence is still evolving. It requires interventional-radiology assessment; potential vascular and non-target tissue injury must be discussed. It does not reconstruct cartilage.
What happens, how long, and what could it cost?
What happens
An interventional radiologist assesses suitability for selective embolization of small arteries around the knee.
When might I notice a change?
A reliable personal timeline cannot be predicted from the evidence reviewed here. Agree on a review date before starting.
How long might benefit last?
Benefit and durability depend on the exact intervention and population. The evidence section below explains what is known.
Repeat treatment
Ask about uncertain durability, alternatives, and how persistent symptoms would be managed.
Activity and recovery
Obtain instructions for the vascular access site, activity, and signs of vascular or tissue complications.
Ask for a complete estimate
Consultation, imaging, embolic material, procedure/facility charges, and follow-up.
Use this as a consultation guide. A timeline is not a guarantee; the evidence and FDA sections below remain part of the decision.
Both groups improved; the between-group difference was not significant at four months. Uncontrolled improvement alone can overestimate treatment benefit.
Supports selected patients after conservative care fails, while calling for larger randomized trials. A society statement is not a treatment guarantee.
Recommends research-only use because efficacy and long-term safety evidence are insufficient. Original guidance was IPG708; its recommendations differ from SIR’s later position.
Editorial synthesis · reviewed September 19, 2026. These are selected decision-relevant references, not an exhaustive systematic review or a new formal evidence grade. FDA status and coverage are assessed separately.
FDA status
Embolic product and use must be checked
FDA regulates the embolic materials used in GAE. The cited Embosphere clearance lists tumors, uterine fibroids, prostatic arteries for BPH, and arteriovenous malformations; it does not list knee osteoarthritis. That record must not be presented as an FDA-cleared knee OA indication. Confirm the exact material and current labeling with the interventional radiologist.
Site summary of FDA information · reviewed September 19, 2026. Refer to current product labeling. This is not an FDA endorsement of this site.What do professional guidelines say?
ACR: No OA guideline recommendation for GAE.
Will Medicare cover it?
UNSURE; policy and case-specific review required. No booking is available here.
Compare nonsurgical knee arthritis care, injection choices, and selected surgical alternatives—with evidence, limits, and questions for your clinician.